
TL;DR

Get health and wellness essentials delivered free with Prime
- Fast, free delivery on millions of items
- Prime Video, Amazon Music and more included
- Member-only deals all year
A qualitative study published in the Journal of Advanced Nursing examined how specialist palliative care nurses make decisions when dying patients become unresponsive. Interviews highlighted close observation, knowledge of patients’ wishes, clinical judgment and family communication, while pointing to a need for stronger training and support.
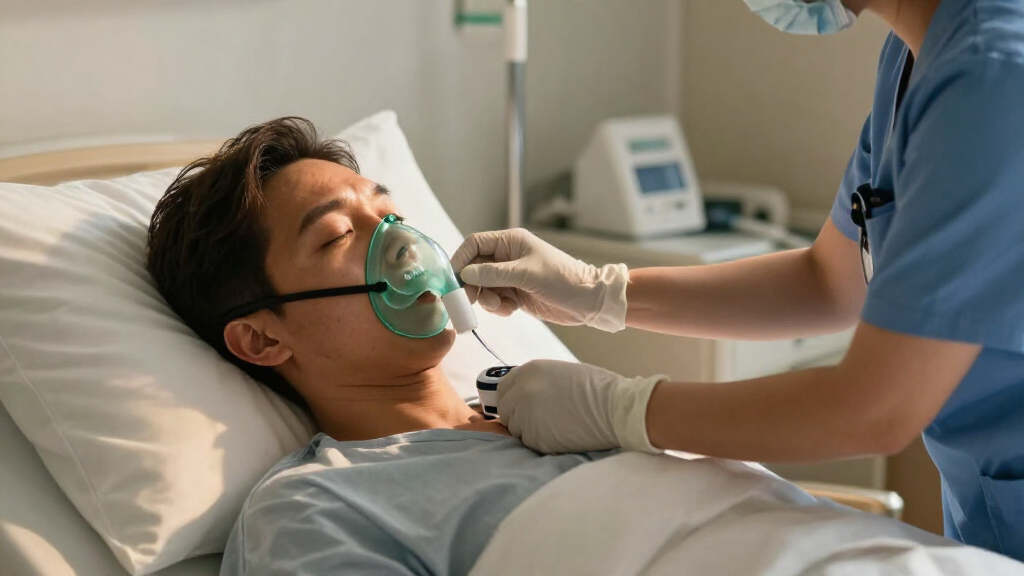
A qualitative study from Flinders University examines how specialist palliative care nurses make decisions when dying patients become unresponsive and can no longer express pain, preferences or fears. Published in the Journal of Advanced Nursing, the research reports that nurses draw on clinical expertise, close observation, ethical judgment and communication with families to guide care in the final days of life.
The researchers interviewed specialist palliative care nurses from a metropolitan palliative care service. Their findings describe decision-making as shaped by patients’ known wishes and cues, assessments of comfort and dignity, the care setting, and engagement with families. Nurses also have to interpret possible signs of distress when a patient cannot explain what they are experiencing.
The paper describes the unresponsive patient as an “absent presence”: although unable to speak, the person’s identity, values and wishes continue to inform decisions. Nurses interviewed said care requires focused attention to the dying process and a willingness to advocate for patients who can no longer advocate for themselves. The study notes that the period from becoming unresponsive to death averages about two days; that figure is presented as context, not as a prediction for an individual patient.
The researchers found that nurses did not explicitly describe the ethical and moral dimensions of their decisions, suggesting these considerations were often handled implicitly. Lead author Tricia O’Connor, a doctoral student at Flinders, said communication, uncertainty and ethical and moral agency affect decision-making. The study calls for stronger preparation and clinical support, including mentorship, reflective discussion, communication skills development and guidance for care.
Keeping Patient Wishes Central
The findings focus on a difficult gap in end-of-life care: patients who are close to death may be unable to report discomfort or confirm what care they want. Decisions then depend on observing possible distress, understanding the person’s known preferences and communicating with those close to them. The study frames these responsibilities as central to safeguarding comfort, dignity and person-centered care.
For health care services, the research points to practical needs across settings, not just specialist palliative care units. Training and structured support could help nurses recognize the unresponsive phase, discuss difficult decisions with families and make the ethical reasoning behind care more explicit. The study identifies these as areas for attention; it does not test whether any particular training program improves patient outcomes.
Products Worth Considering

Therabody Theragun Mini 3rd Generation Massage Gun, Black

Therabody SmartGoggles 2nd Gen Heated Eye and Temple Massager

Therabody Theragun Relief Massage Gun, 3-Speed, Navy
As an affiliate, we earn on qualifying purchases.
How Nurses’ Decisions Were Studied
The study, titled “When Dying Patients Fall Silent: How Nurses Navigate Decision-Making in the Last Days of Life—A Qualitative Study,” was led by Tricia O’Connor and included study co-author Catherine Paterson, a professor of cancer nursing at Flinders’ Lifewell Cancer Research Centre. It was published in the Journal of Advanced Nursing in 2026 (DOI: 10.1111/jan.70766).
Because the research used interviews with specialist nurses from one metropolitan palliative care service, it reports those nurses’ experiences and perspectives. The supplied report does not give the number of participants or establish how closely their experiences reflect nursing practice in other regions, specialties or care settings. Its recommendations for education and clinical frameworks are proposals based on the findings, rather than evidence that such measures have already been adopted.
““Patients die in many different health care settings, but building relationships with a patient and their family greatly informs and influences nurses’ decision-making.””
— Tricia O’Connor, study lead author and doctoral student at Flinders University
Limits of the Interview Findings
The report does not specify how many nurses took part, and the participants came from a single metropolitan service. It is not clear from the supplied material whether nurses in other settings face the same decision-making challenges or would prioritize the same supports. The qualitative findings describe experiences; they do not measure the effects of specific training, mentorship or guidelines on care or patient outcomes.
The study also does not provide a clinical checklist for identifying pain or distress in an unresponsive patient, nor does it set out a universal rule for resolving disagreements about care preferences. Individual circumstances and available information may differ. The researchers’ call for frameworks is a recommendation, not confirmation that new guidelines have been issued.
Calls for Training and Guidance
The researchers say health care leaders, educators and policymakers should strengthen nurses’ preparation for caring for unresponsive dying patients across care settings. Their suggested areas include structured mentorship, reflective dialogue, communication skills development and clearer support for discussing ethical decisions. They also call for clinical guidelines or frameworks to help nurses navigate this phase of dying.
The report does not announce a rollout, timetable or policy change. The next step, if health services act on the recommendations, would be developing and evaluating training and guidance; the supplied material gives no details about planned implementation or follow-up research.
Key Questions
What did the Flinders University study examine?
It examined how specialist palliative care nurses make decisions when dying patients become unresponsive, using interviews with nurses from a metropolitan palliative care service.
What did nurses consider when patients could no longer communicate?
The study describes nurses drawing on clinical expertise, close observation, patients’ known wishes and family communication to assess care needs, including comfort and dignity.
What does the study mean by an “absent presence”?
It describes how a patient’s identity, values and wishes can continue to shape care even when the patient is unable to speak for themselves.
Does the study show that a particular training program improves care?
No. The research reports interview findings and recommends stronger education and clinical support. The supplied report does not describe a trial measuring the effects of a specific program.
What support do the researchers recommend?
They point to structured mentorship, reflective discussion, communication skills development and clinical guidance that helps nurses address the ethical dimensions of decisions.
Source: medicalxpress.com