
TL;DR

Get health and wellness essentials delivered free with Prime
- Fast, free delivery on millions of items
- Prime Video, Amazon Music and more included
- Member-only deals all year
Medical educators at an October 15 summit said students’ use of AI is not automatically cheating when it is brought into the open and used properly. They also warned that reliance on AI could weaken clinical skills, and argued training should include situations where the technology is unavailable.
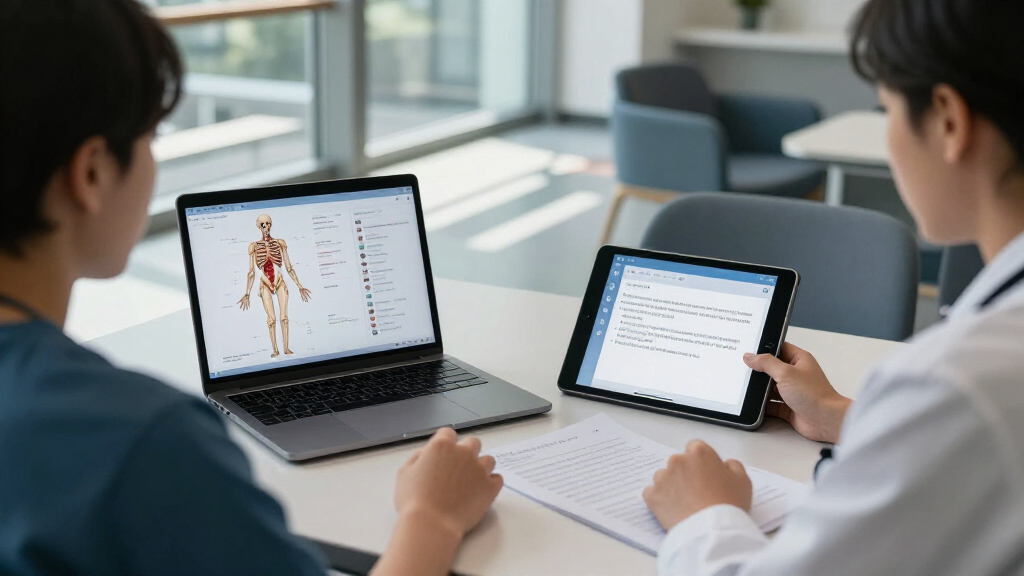
Medical educators at the Association of Health Care Journalists Fall Summit in Los Angeles said on October 15 that using AI for medical school assignments is not automatically cheating, while warning that students still need to learn clinical reasoning without it. Their discussion highlights a challenge for medical schools: teaching students to use AI openly while preparing them to make decisions when the technology is unavailable or its output needs to be questioned.
Graciela Gonzalez-Hernandez, a professor and vice chair for research and education in computational biomedicine at Cedars-Sinai Medical Center, said AI use can be part of coursework when handled transparently. She described asking students to show how they construct prompts, share the paragraphs AI produces and work through the results together. Her approach treats AI use as something to teach and discuss rather than something students should conceal.
Gonzalez-Hernandez said that time spent hiding AI use from instructors would be better spent learning how to use the tools properly. She argued that AI will be part of education and that classroom discussion can help students understand its role. Her comments address whether AI use itself constitutes cheating; they do not establish a universal policy for medical schools or say that every use is acceptable.
The speakers also discussed the risk of students losing skills through dependence on AI. Tina Hernandez-Boussard, a Stanford professor of biomedical informatics, described a group of medical residents who traveled to a hospital cardiac ward in Uganda. When the electricity failed and AI was unavailable to interpret electrocardiograms, she said, the residents struggled to synthesize the information confidently enough to make patient care decisions. She presented the episode as a warning about maintaining skills when technology fails.
Keeping Clinical Judgment With Trainees
The debate matters because medical students are learning skills that affect decisions about patient care, while AI tools may increasingly shape how they study and approach clinical information. If students rely on AI without learning to assess its responses, they may be less prepared when a tool is unavailable or when its answer needs scrutiny. The Uganda example, as described by Hernandez-Boussard, illustrates that concern, though the report does not provide details that would establish how broadly it applies.
Gonzalez-Hernandez also said AI could help clinicians notice questions or perspectives they might otherwise miss. She pointed to differences in how patient symptoms are described in clinical notes, arguing that language can convey doubt and that such doubt may vary across patient groups. In her view, AI could prompt clinicians to reconsider omissions and help counter that imbalance. The discussion presents this as a potential benefit, not evidence that AI reliably removes bias.
For students and educators, the practical issue is how to teach both use and judgment: students need to understand what AI can contribute, while retaining the ability to reason without it and evaluate what it produces. The summit discussion did not resolve how schools should assess those abilities or set rules for assignments.
Products Worth Considering

Fitbit Sense Health & Fitness Smartwatch (White/Gold, International Version)

Garmin Forerunner 570 GPS Running Smartwatch, 47mm, Aluminum, Black

Oura Ring 4 Smart Ring – Silver – Size 8
As an affiliate, we earn on qualifying purchases.
A Classroom Policy Debate
The remarks came during a session at the Association of Health Care Journalists Fall Summit, held in Los Angeles. Gonzalez-Hernandez spoke from her experience leading an academic program that she said is friendly to AI use. She described assignments in which students share prompts and AI-generated text so the work can be examined together.
Eli Cahan, MD, MSc, a session moderator and investigative journalist who is also a Stanford neonatal intensive care fellow, raised a broader question: which forms of clinical reasoning must doctors perform themselves, and which might AI handle accurately? He compared navigation before and after GPS, but said he was withholding judgment about what reasoning skills remain necessary for physicians. The comparison framed a question for educators; it did not establish that clinical reasoning can safely be handed over to AI.
The summit report focused on the educators’ comments and examples. It did not describe a new medical school rule, a formal professional standard, or research measuring the effects of AI use on students’ clinical skills.
“I’m withholding judgment until we see whether and what kind of clinical reasoning actually is relevant for doctors to do.”
— Eli Cahan, session moderator
How Schools Will Set AI Rules
The summit report does not say whether medical schools have adopted common rules for AI-assisted coursework, how instructors should distinguish acceptable help from misconduct, or how student work should be evaluated when AI is involved. It also gives no outcome data establishing whether AI use has caused a measurable decline in clinical reasoning among medical students or residents.
The residents’ experience in Uganda was offered as an example of possible de-skilling, but details about the group, the circumstances and the extent of the difficulty were not provided. Gonzalez-Hernandez’s suggestion that AI could help counter bias in clinical notes was likewise presented as a possibility; the report does not cite evidence showing how well it works in practice. Cahan’s question about which reasoning tasks doctors must perform themselves remains open.
Training for AI and Outages
The educators’ comments point toward two areas for medical training: teaching students to disclose and examine AI use, and practicing clinical tasks without technological assistance. Gonzalez-Hernandez said training should include scenarios using paper and pencil. The summit report did not announce a schedule for implementing those methods or identify a next policy decision by a school or professional body.
Further evidence and institutional guidance will be needed to clarify which uses schools permit, how students’ independent reasoning should be assessed, and how AI’s role should be evaluated in clinical settings. For now, the discussion offers a set of competing considerations rather than a settled standard: AI may support learning and prompt clinicians to consider missed questions, while students still need to synthesize information when tools are unavailable.
Key Questions
Did the educators say using AI in medical school is cheating?
Not automatically. Gonzalez-Hernandez said AI is not plagiarism and described assignments where students share their prompts and AI-generated text for classroom discussion. The report does not set a rule for every school or assignment.
Why are some educators concerned about AI use?
They are concerned students may lose the ability to reason through clinical information without AI. Hernandez-Boussard described residents who struggled to interpret cardiac information after losing power at a hospital in Uganda.
Could AI help doctors notice bias?
Gonzalez-Hernandez said AI might prompt clinicians to ask questions they missed and help address differences in how patient symptoms are described. The report presents this as a potential benefit, not a proven result.
Have medical schools adopted a shared policy?
The summit report does not identify a common policy or describe a new standard. It leaves open how schools will define acceptable use and assess students’ independent clinical reasoning.
Source: rss